
Contact Info
Phone: 470-322-6757
Fax: 770-339-9804
Fax: 770-339-9804
Meet with us
631 Professional Drive, Suite 300
Lawrenceville, Georgia 30046
Lawrenceville, Georgia 30046


Told breast reconstruction is too risky? Dr. Schwartz explains how Goldilocks mastectomy with a LICAP flap may offer selected women with larger breasts another option, including when radiation is part of treatment.
If you are getting ready for a mastectomy, you may have heard some hard words.
Maybe a doctor said your weight makes reconstruction “too risky.” Maybe you were told that your breast size or other health problems limit your options. Maybe you need radiation, and you worry that reconstruction is no longer possible. Or perhaps no one has explained your choices at all.
If this sounds familiar, I want you to know something: wanting to feel comfortable in your body after cancer surgery is normal. You are not asking for too much.
For some women with larger bodies and larger breasts, an approach called Goldilocks mastectomy with a LICAP flap may offer another choice. It uses your own nearby skin and fat to rebuild a breast shape, sometimes completing the mastectomy and reconstruction in one operation.
Two common approaches to breast reconstruction are:
Both can work well. But obesity, diabetes, smoking, and other health conditions can increase the chance of problems such as infection, delayed wound healing, or loss of the reconstruction.
Postmastectomy radiation therapy, often called PMRT, adds another consideration. Radiation treats cancer cells that may remain after surgery, but it can also affect the skin and reconstructed breast. With implants, it can increase the risk of capsular contracture—tightening of scar tissue around the implant—and reconstruction failure. Your own tissue can also develop changes in firmness, shape, or volume after radiation.
These risks deserve a careful discussion. They do not automatically mean that every type of reconstruction is ruled out.
Goldilocks reconstruction with a LICAP flap combines two techniques during the same operation. Together, they use tissue from the breast area and side of the chest to create a breast mound.
During the mastectomy, the surgeon removes the breast tissue needed for cancer treatment. When it is safe to do so, some of the overlying skin and the fatty tissue beneath it can remain.
The surgeon removes the outer skin layer from selected areas—a step called de-epithelialization—then folds and shapes the remaining tissue into a breast mound.
This is a form of autologous breast reconstruction, because it uses your own tissue.
The Goldilocks approach can offer a middle option between an aesthetic flat closure, which creates a smooth chest without a breast mound, and more extensive reconstruction.
On its own, however, Goldilocks reconstruction may not provide as much breast volume as a woman would like. That is where the LICAP flap can help.
LICAP stands for lateral intercostal artery perforator. The name describes the small blood vessels that supply tissue along the side of the chest.
Many women have extra skin and fat in this area, near the armpit and bra line. A LICAP flap moves some of that tissue into the breast while keeping it attached to its blood supply.
This is called a local pedicled flap. Unlike a DIEP free flap, it does not require transferring tissue from the abdomen and reconnecting blood vessels with microsurgery. It also leaves the underlying muscle in place.
The added tissue can:
In 2019, I published results from 14 women who underwent bilateral Goldilocks mastectomy with LICAP flap reconstruction, involving 28 breasts.
All patients completed reconstruction and healed by 10 weeks. There was no complete flap loss, and no flap necrosis requiring another operation. However, healing problems did occur: six breasts had wound complications that healed with conservative care, two donor sites needed wound care, and four breasts developed fat necrosis—areas where fatty tissue becomes damaged and may form firm lumps.
The mastectomies and reconstruction were performed in the same operation. We also used free nipple grafting: the nipple and areola were removed and placed onto the reconstructed breast when appropriate for cancer safety. This differs from nipple-sparing mastectomy, in which the nipple remains attached to its original tissue and blood supply.
Since that publication, my experience has grown to more than 50 patients, as described in my accepted letter to the editor. That larger experience has not yet been published as a full outcomes study.
My technique has also evolved. I now generally use a more limited amount of tissue from the lateral chest because the larger, extended flaps used earlier were more prone to fat necrosis.
In September 2026, surgeons in Washington, DC, published a report in Plastic and Reconstructive Surgery describing the combined approach in four patients.
They reported satisfactory breast volume and contour, with no flap loss or major complications. These are encouraging findings, particularly for women whose medical conditions make more extensive surgery difficult.
Still, four patients represent a small study. Larger studies and longer follow-up are needed to understand the results more fully.
I submitted a letter discussing my earlier publication and subsequent experience. The letter has been accepted but has not yet been formally published. It also discusses nipple options, including free nipple grafting and immediate nipple reconstruction, which creates a nipple shape from local skin during the same operation.
Needing radiation does not automatically mean you cannot have breast reconstruction. It does mean your surgical plan should be coordinated with your radiation oncologist.
In my practice, I have seen encouraging results with Goldilocks and LICAP reconstruction in selected women with obesity, large breasts, and breast ptosis—the medical term for breasts that droop or hang low—who need radiation after mastectomy.
My experience suggests that some of these women can maintain a satisfactory breast shape after radiation and may not need another reconstructive operation.
I am preparing a study to share these findings. Until those results are published and reviewed, they should be understood as my clinical experience, rather than proof that this approach is safer or more durable than other methods.
Radiation can still cause firmness, shrinkage, fat necrosis, or changes in appearance. No reconstruction is immune to those effects. Your care team should discuss both the potential benefits and the uncertainties with you
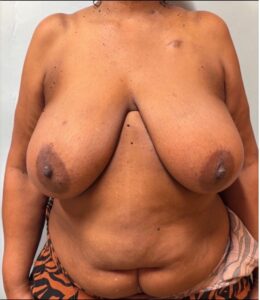
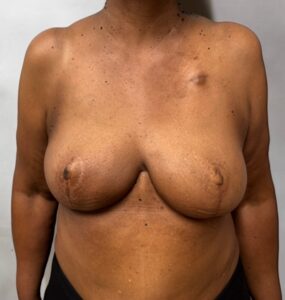
Figure 1. 51-year-old woman with a higher body weight with right breast cancer, macro.mastia and ptosis who requires post-mastectomy radiotherapy. She refuses both implant-based reconstruction and free tissue transfer from the abdomen.
Figure 2. The patient is shown 6 months after the completion of post-mastectomy radiotherapy after her bilateral Goldilocks Mastectomy, LICAP flap and CV flap nipple reconstruction.
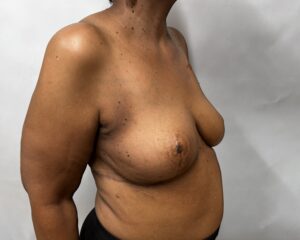
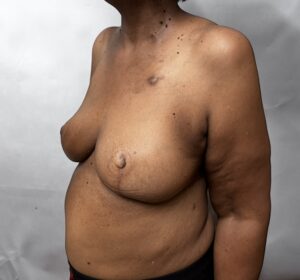 Figure 3. The well-healed right LICAP donor site is demonstrated. Note that the donor site ends at the anterior edge of the latissimus dorsi muscle, not to violate this reconstructive option.
Figure 4. The well healed left LICAP donor site is demonstrated. LICAP flap harvest allows for both increasing the volume and size of the reconstructed breast and improving the contour of the lateral chest wall.
This reconstruction generally works best when there is enough nearby skin and fat to create a breast mound.
It may be worth discussing if you:
If you need radiation, this approach may still be considered as part of an individualized treatment plan. Radiation itself does not make someone a good candidate; your anatomy, health, and cancer treatment needs all matter.
Women with smaller breasts or little excess tissue may not have enough tissue for the breast volume they want. Another approach may better meet their goals.
Every reconstruction involves trade-offs. An honest conversation helps you know what to expect.
For some women, one operation provides a result they are comfortable with. For others, reconstruction involves more than one step.
You do not need to know all the medical terms before your appointment. You can bring these questions with you:
If you have been told reconstruction is not possible, it is reasonable to seek a second opinion from a surgeon experienced in these techniques.
Hearing “no” to one type of reconstruction can feel like hearing “no” to every possibility. Sometimes, there are other options worth exploring.
Your body size should be part of a thoughtful medical assessment, and you deserve a clear explanation of which choices may be safe for you and why.
Some women choose reconstruction. Some choose aesthetic flat closure. Some need more time to decide. There is no single way you are supposed to look or feel after breast cancer.
My goal is to help you understand your options, feel heard, and make a decision that fits your health and your life.
— Jean-Claude D. Schwartz, MD, PhD
This article provides general education and does not replace medical advice. Surgical eligibility, risks, and results vary. Discuss your options with your breast surgeon, reconstructive surgeon, and oncology team.
 Dr. Schwartz is a highly respected national leader in oncoplastic breast surgery. As a breast surgeon and reconstructive surgeon, he performs most mastectomies and reconstructions in one surgery, saving his patients time and money by seeing only one expert, paying only one set of deductibles and co-pays, and most importantly, reducing time spent in the operating room while providing unparalleled results.
Dr. Schwartz and his entire staff specialize in breast surgeries only, and as such, are highly experienced in dealing with insurance companies. They can provide guidance and invaluable information to women undergoing breast reconstructive surgeries. Additionally, as part of the Northside Hospital system, patients benefit beyond Dr. Schwartz’s practice.
Dr. Schwartz is always accepting new patients diagnosed with breast cancer and makes it his priority to see them immediately, despite his very busy schedule. He is a preferred provider for the majority of insurance plans and is highly recommended by insurance companies and patients alike. By performing most of his surgeries in an outpatient ambulatory center, he saves his patients on hospital costs, co-pays, and more.
Click to SCHEDULE YOUR CONSULTATION TODAY!
